What the Anion Gap Measures
The anion gap is a helpful way to interpret electrolytes from a serum chemistry panel and approximate the quantity of unmeasured anions in the blood. It assists clinicians evaluate acid-base balance and identify patterns that may point to a metabolic disorder. An increased or low result does not diagnose a disease on its own, but it gives important clues that guide clinical interpretation.
An anion gap calculator is a handy diagnostic tool because it turns common lab values into a useful number. The calculation uses the major measured ions in an electrolyte panel to suggest whether there is an excess of acids, a deficiency of proteins, or another variation affecting the body’s chemistry. In routine practice, it is most often used to evaluate metabolic acidosis and differentiate between different causes of a disturbed acid-base state.
Most of the time, the gap shows the balance between positive ions and negatively charged ions. Because some important ions are not directly measured on standard blood test results, the result helps reveal hidden changes in the blood. That is why the anion gap is so important for diagnosis support, especially when symptoms are nonspecific and the blood test results need a careful look.
Anion Gap Formula and Inputs
The primary anion gap formula uses 3 typical lab values: sodium, chloride, and bicarbonate. In its simplest form, it appears as:
Anion gap = sodium - (chloride + bicarbonate)
These values are usually taken from serum chemistry tests. More specifically, you may see serum sodium, serum chloride, and serum bicarbonate shown in the report. Because these are standard components of the chemistry panel, the calculation can be done easily with the help of an anion gap calculator or by hand for review.
Some laboratories may use slightly different methods or reporting conventions. Some include potassium in the formula, while others do not. For everyday use, the sodium-based version is the most common. What matters most is that you use the same method as the lab reference range or reference interval included in the report, since that affects how the result is interpreted.
To calculate anion gap accurately, make sure the input values come from the same sample and the same time point. Inconsistent or previous lab values can produce a misleading number. This is especially important when monitoring a changing acid-base disorder or following treatment for a metabolic acidosis.
How to Operate an Anion Gap Calculator
A calculator for the anion gap is easy to use, but the nuances matter. A sequential calculation helps reduce mistakes and makes the result simpler to interpret in context. Start with the sodium value, then subtract the sum of chloride and bicarbonate. The number you get is the estimated amount of unmeasured anions.
This is a practical approach:
- Find the serum sodium value from the electrolyte panel. Find the serum chloride value. Locate the serum bicarbonate value. Add chloride and bicarbonate together. Subtract that total from sodium.
This step-by-step calculation is the same method used by many online and clinical medical calculator tools. The main benefit of a calculator is speed, but the real value comes from understanding what the number means once you have it.
Always compare the result with the lab’s reference range. A number that seems mildly off in one setting may be expected in another, depending on the laboratory method and whether the patient has low albumin. Good clinical interpretation requires both the result and the clinical story.
Typical vs Elevated Anion Gap
A within-range anion gap suggests that the equilibrium between measured positive ions and measured negative ions is as expected. A increased anion gap suggests that additional unmeasured acids are probably present, which commonly indicates a form of elevated anion gap metabolic acidosis.
On the other hand, a normal result does not necessarily mean everything is fine. Some patients with normal-gap metabolic acidosis still have a important acid-base disorder, often due to bicarbonate reduction or chloride accumulation. This is why test interpretation should always consider the full profile of electrolytes, not the gap alone.
A high gap is especially helpful for identifying hidden acid accumulation. In acidemia-related metabolic disturbance, the anion gap can indicate causes such as lactate buildup, ketones, kidney dysfunction, or certain toxins. A normal gap can instead suggest a different metabolic pattern that needs another diagnostic pathway.
The key point is that the anion gap is a pattern-based tool. It assists the clinician by showing whether the blood chemistry aligns with a high gap or low gap profile, and that can sharpen the list of possible causes efficiently.
Typical Causes of a Elevated Anion Gap
A high anion gap metabolic acidosis develops when acids collect in the blood and lead to extra unmeasured anions. Various common conditions can do this, and the clinical context usually helps distinguish among them.
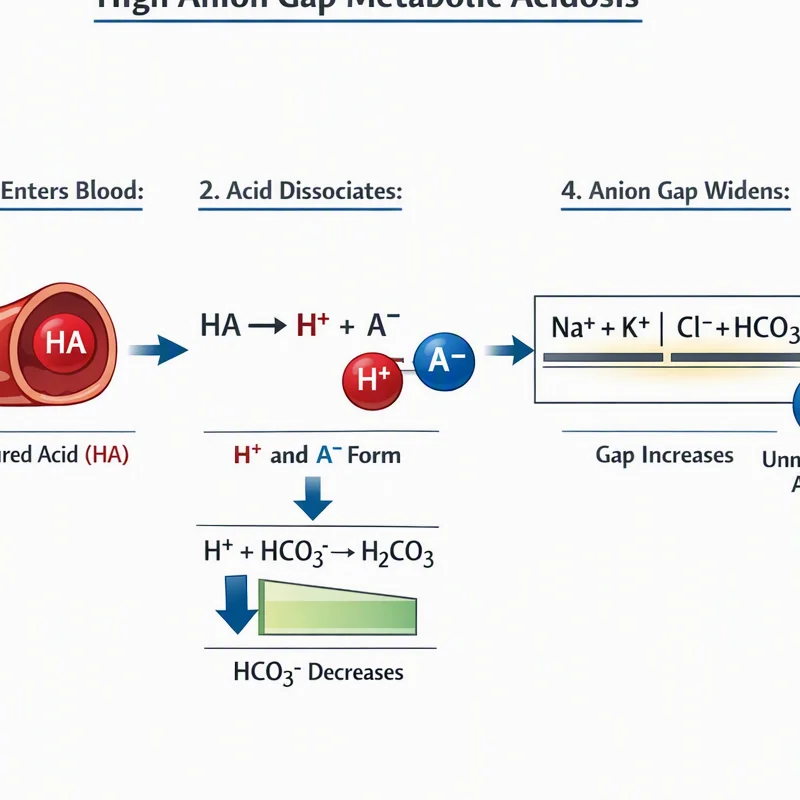
Lactic acidosis is one of the most common causes. It can occur when tissues are not obtaining enough oxygen, when severe infection is present, or when metabolism is otherwise stressed. In this setting, lactate increases and the gap rises.
Ketone acidosis is another major cause. It can develop when the body breaks down fat for fuel and produces ketone acids. This pattern is often seen with uncontrolled diabetes, prolonged fasting, or heavy alcohol use. The exact cause depends on the overall presentation, but the anion gap often becomes clearly elevated.
Reduced kidney function can also cause a high gap because the kidneys are less able to clear acids from the body. As acid retention increases, the gap may rise progressively. This makes the anion gap a useful marker when evaluating kidney-related metabolic changes.
Toxins are another important category. Certain ingestions and exposures can produce an elevated gap by introducing acids or toxic metabolites. Salicylates are a classic example and should be considered when the lab pattern and symptoms fit. Because toxin-related causes can be serious, an unexpected high gap should prompt careful review of medication history, exposures, and accompanying symptoms.
Decreased Anion Gap Causes and Clinical Meaning
A low anion gap is less frequent than a elevated one, but it still is important. In many cases, the initial step is to consider lab error or a specimen issue, because inaccurate measurements are one of the most frequent explanations. Running the test again can clarify whether the abnormality is true.
Hypoalbuminemia is a key true cause of a low gap. Albumin is a anionic protein, so when its level falls, the calculated gap may also drop. This is one reason the measured https://anion-gap-calculation.com/calculators/corrected-anion-gap.html number can underestimate the real acid load if albumin is not considered.
Multiple myeloma is another important cause because abnormal proteins in the blood can affect the distribution of charged particles. In some patients, this changes the anion gap enough to be noticeable on routine chemistry testing. A low result does not confirm the diagnosis, but it may provide a signal that prompts further evaluation.
Other causes include changes in measured ions or interference from unusual substances. The practical message is that a low gap should not be dismissed. It may reflect lab error, low protein states, or a condition that requires more workup. If the value is unexpected, repeat testing and broader medical interpretation are often appropriate.
Albumin Correction and Adjusted Anion Gap
As albumin is a important unmeasured anion, it strongly affects the formula. This is why an anion gap calculator is most accurate when it includes albumin correction or when the clinician corrects the result manually. The corrected anion gap assists estimate the actual acid-base picture when albumin is low.
The logic for this reference correction is simple: low albumin reduces the measured gap even if substantial acids are present. Without correction, the result may appear normal when it is not. That can mask high anion gap metabolic acidosis and slow recognition of the real problem.
Albumin correction is a form of clinical interpretation that improves accuracy. It is especially important in patients with chronic illness, inflammation, malnutrition, or liver-related changes in protein levels. In these settings, the uncorrected number can be inaccurate.
Various clinicians and laboratories may follow slightly different correction factors, so the main principle is to recognize that low albumin lowers the gap. If albumin is abnormal, a corrected value gives improved diagnosis support than the raw result alone.
In What Way Does Anion Gap Fit into Acid-Base Disorders
This anion gap is one piece of the broader assessment of an acid-base disorder. It is particularly useful in metabolic acidosis, where it helps distinguish high gap from normal gap patterns. That distinction changes the differential diagnosis and the next steps in evaluation.
Respiratory compensation is part of the body’s adjustment to metabolic acid buildup. When acidosis is present, breathing may become faster or more forceful to help lower carbon dioxide and partially offset the pH change. The anion gap does not measure compensation directly, but it helps identify the primary metabolic problem that causes it.
The delta gap is another useful concept. It compares the change in the anion gap to the change in bicarbonate and helps reveal mixed disorders. For example, a patient may have a high gap acidosis plus another hidden metabolic issue at the same time. That is why the gap should be interpreted with the bicarbonate level, pH when available, and the overall electrolyte pattern.
In practice, the anion gap works best as a diagnostic tool. It does not replace full evaluation, but it gives structure to the analysis of acid-base balance and helps identify whether the pattern is more consistent with acid gain, bicarbonate loss, or a combined disturbance.
Frequently Asked Questions About Anion Gap Calculation
What is the anion gap calculation from lab values?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In other words, take serum sodium and subtract serum chloride plus serum bicarbonate. An anion gap calculator can do this automatically, but the manual step-by-step calculation is easy to follow and helps with lab interpretation.
What counts as a normal anion gap range?
The lab reference range depends on the testing method used by the laboratory, so the exact reference interval can vary. In general, a result within the lab’s stated range is considered a normal anion gap. Always interpret the number using the specific report rather than assuming a universal cutoff.
Why is albumin used to correct the anion gap?
Albumin has a negative charge and is a major undetected anion. When albumin is low, the measured gap can seem falsely low even if acid is present. Albumin correction offers a more precise corrected anion gap and enhances clinical interpretation, especially when evaluating metabolic acidosis.
What does a high anion gap mean?
A high anion gap usually points to extra acids or additional anions in the blood. Common causes include lactic acid buildup, ketone-related acidosis, kidney failure, and certain toxins, including salicylates. It is a sign that often raises concern for high anion gap metabolic acidosis.
Can a low anion gap be a sign of a serious condition?
Certainly. A low anion gap can reflect hypoalbuminemia, plasma cell myeloma, or sometimes laboratory error. Though it may be less urgent than a significantly elevated gap, it can still point to an significant condition and should be assessed in context with other test results and the full clinical picture.
When Medical Evaluation Is Needed
Shifts in the anion gap should consistently be assessed alongside symptoms and the complete range of laboratory data. If a person has signs of severe illness, confusion, rapid breathing, dehydration, persistent vomiting, chest pain, or worsening weakness, they may need immediate care. These signs can occur with significant acid-base problems and should not be overlooked.
Urgent test results warrant immediate evaluation, especially if the values indicate significant acid buildup, kidney dysfunction, or toxic exposure. A worrisome trend on the chemistry panel should lead to a timely medical evaluation instead of delaying for signs to progress.
An anion gap is a valuable assessment and analysis tool, but it is not a definitive diagnostic. If you are using an anion gap calculator and the result seems off, the most appropriate next step is to review the findings with a qualified clinician. This is particularly relevant when the result is paired with low or high bicarbonate, kidney issues, concern for ingestion, or signs of metabolic acidosis.